
Alpha-Gal Symptoms Hours After Eating Red Meat: Why You Wake Up With Hives at Night
Alpha-Gal Symptoms Hours After Eating Red Meat: Why You Wake Up With Hives at Night The fast answer: If hives, intense itching, or stomach…
How often is a large local reaction to a sting misdiagnosed as cellulitis and treated with antibiotics? The joined data: prescribing rates, reaction prevalence, the 24–48h vs 48–72h timeline, and hospital misdiagnosis rates.
Source: BMJ Open (Finnikin et al., 2023) (2023)
A sting swells, reddens and keeps growing for two days. Is it an allergic large local reaction doing exactly what large local reactions do — or cellulitis, a bacterial infection that needs antibiotics? Clinicians get this wrong often enough that both ends of the mistake have been measured: how often bite and sting presentations leave with an antibiotic, and how often hospital ‘cellulitis’ turns out not to be cellulitis at all. This page joins those datasets — prescribing rates, large-local-reaction prevalence, the reaction-versus-infection timeline, and hospital misdiagnosis rates — in one place, with every figure’s scope labelled, because no single study measures the whole pathway.
Two safety rules come before every number. First, trouble breathing, throat tightness, widespread hives, dizziness or collapse after a sting is anaphylaxis, not a local reaction: use an epinephrine auto-injector if one is available and call emergency services immediately. Second, nothing on this page is a reason to stop or skip an antibiotic you have been prescribed — some reactions really are infected. What the data can do is help you understand the difference, and have a better conversation with the clinician treating you. If redness is spreading, you have a fever, red streaks are tracking away from the sting, or pain is increasing rather than easing, seek medical care promptly.
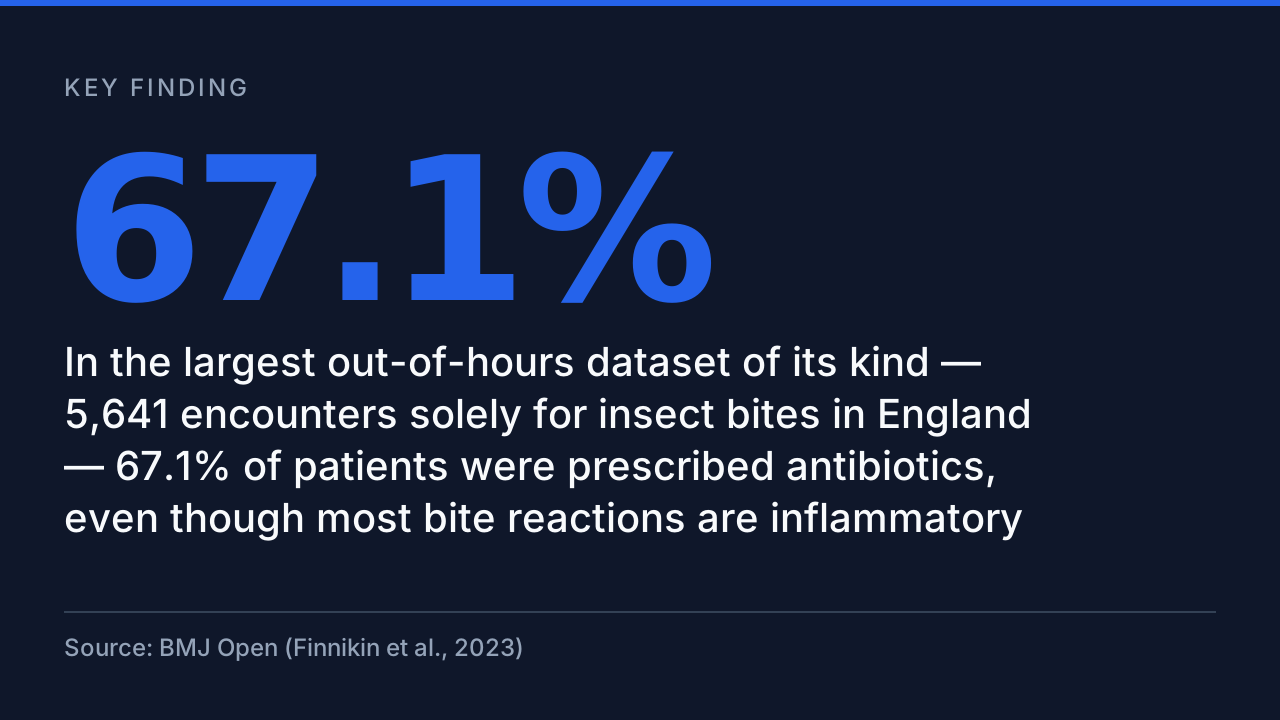
Far more often than the infection rate can explain. In the largest out-of-hours dataset of its kind — 5,641 encounters solely for insect bites in England — 67.1% of patients were prescribed antibiotics (BMJ Open (Finnikin et al., 2023), 2023), and the authors’ extrapolation puts insect-bite consultations in England at 1.5 million a year. A separate audit of ten UK general practices found the same pattern in daytime care, with 74.7% of bite patients receiving an antibiotic (Family Practice (Wilcock et al., 2023), 2023). Yet the guideline consensus, restated in the newest UK guidance, is that most bite reactions are inflammatory rather than infected — which means a large share of those prescriptions were written for reactions, not infections.
| METRIC | VALUE | SOURCE |
|---|---|---|
| Out-of-hours bite encounters prescribed antibiotics | 67.1% | BMJ Open (Finnikin et al., 2023) |
| Prescribing rate, general practitioners | 60.5% | BMJ Open (Finnikin et al., 2023) |
| Prescribing rate, advanced nurse practitioners | 71.1% | BMJ Open (Finnikin et al., 2023) |
| Bite patients prescribed antibiotics, 10-practice audit | 74.7% | Family Practice (Wilcock et al., 2023) |
| Flucloxacillin share of bite antibiotic prescriptions | 82.1% | BMJ Open (Finnikin et al., 2023) |
| Estimated bite consultations per year, England | 1.5 million | BMJ Open (Finnikin et al., 2023) |
Two features of the dataset deserve emphasis. The first is what triggered prescriptions: swelling and spreading are precisely what a large local reaction produces as it follows its normal course, so the reaction’s own signature reads as infection’s warning sign. The second is the scope label. These are English out-of-hours data on insect bites — the BMJ Open cohort explicitly excluded stings and infestations — so they measure the clinic-door behaviour around bites, the closest verified proxy for the sting presentations this site covers. The audit tells the same story in ordinary daytime practice: across ten practices, bite prescriptions accounted for 5.1% of all flucloxacillin prescribing on average, rising to 10.7% at the July peak, and 12% of patients came back for a second look. StingHelp’s own guidance on when a bug bite genuinely needs antibiotics sets out the infection signs clinicians are weighing at that moment.
A large local reaction is the allergic swelling that follows some stings: by definition it reaches at least 10 cm across and persists beyond a day (European Journal of Case Reports in Internal Medicine (Damanti et al., 2016), 2016). How often it happens depends heavily on who is counted and how strictly the definition is applied. The lowest published estimate puts it at 2.4% of stung people; most adult studies report between 5% and 15%; and some studies report as high as 26% (Polish Archives of Internal Medicine (Nittner-Marszalska & Cichocka-Jarosz, 2015), 2015). No single one of those numbers is ‘the’ prevalence — the range is the honest answer, and the reason for it is in the analysis below.
| METRIC | VALUE | SOURCE |
|---|---|---|
| Minimum diameter in the large-local-reaction definition | 10 cm | European Journal of Case Reports in Internal Medicine (Damanti et al., 2016) |
| Lowest reported prevalence after Hymenoptera stings | 2.4% | European Journal of Case Reports in Internal Medicine (Damanti et al., 2016, citing Severino et al., 2009) |
| Upper end reported by most adult studies | 15% | Polish Archives of Internal Medicine (Nittner-Marszalska & Cichocka-Jarosz, 2015) |
| Highest prevalence reported in some adult studies | 26% | Polish Archives of Internal Medicine (Nittner-Marszalska & Cichocka-Jarosz, 2015) |
| Highest reported frequency among beekeepers | 38% | Polish Archives of Internal Medicine (Nittner-Marszalska & Cichocka-Jarosz, 2015) |
The spread is not sloppiness; it is arithmetic. A study that requires swelling above the 10 cm threshold, lasting more than a day, in adults stung once, will count a fraction of the cases found by a study that accepts any dramatic swelling in people stung for a living. That is why beekeepers, stung repeatedly across a season, sit at the top of the range at up to 38%. For a reader working out which pattern their own swelling matches, StingHelp’s comparisons of skeeter syndrome versus cellulitis and a large local reaction versus anaphylaxis cover the look-alike conditions in detail. The practical takeaway is narrower than the literature: large local reactions are common enough — somewhere between roughly one in forty and one in four stung people, depending on how they are counted — that any clinician seeing sting swelling weekly is seeing them constantly, whether or not they are named.
The cleanest separator in the data is not how the swelling looks — it is when it does what. A large local reaction appears within minutes to hours of the sting and keeps worsening over the first 48 hours, then plateaus and fades, sometimes taking up to 10 days to settle fully (Tropical Medicine and Infectious Disease (2024 review of fire-ant envenomation sequelae), 2024). A true secondary bacterial infection runs on a different clock: guidance puts its typical arrival at 48 to 72 hours after the bite, usually entering through scratched or broken skin (Nottinghamshire Area Prescribing Committee, Insect Bites and Stings Guidance v1.0 (ratified July 2026), 2026). On day one the two overlap almost completely. By day three, their trajectories have usually separated — one easing, one declaring itself.
| METRIC | VALUE | SOURCE |
|---|---|---|
| Large local reaction keeps worsening for | 48 hours | European Journal of Case Reports in Internal Medicine (Damanti et al., 2016) |
| Large local reaction can persist up to | 10 days | Tropical Medicine and Infectious Disease (2024 review of fire-ant envenomation sequelae) |
| True secondary infection typically arises by | 72 hours | Nottinghamshire Area Prescribing Committee, Insect Bites and Stings Guidance v1.0 (ratified July 2026) |
| Guideline minimum bite age before antibiotics are considered | 48 hours | Nottinghamshire Area Prescribing Committee, Insect Bites and Stings Guidance v1.0 (ratified July 2026) |
This is the discriminator the rest of the data hangs on. The newest UK prescribing guidance builds its rule on exactly this gap: an antibiotic is considered only once a bite is at least 48 hours old, with clear signs of infection and at least three listed criteria present (Nottinghamshire Area Prescribing Committee, Insect Bites and Stings Guidance v1.0 (ratified July 2026), 2026) — a rule reported here as guidance, not as advice to any individual reader. The published case literature shows what happens without the timeline. In one documented case, a woman whose hand and forearm swelled dramatically after a wasp sting was treated with antibiotics for a presumed soft-tissue infection, without benefit, before the swelling was recognised as a large local reaction and settled quickly on anti-allergy treatment. Her course — onset within hours, worsening across the first two days — was the reaction’s textbook timeline, read as infection. StingHelp’s day-by-day references, the wasp sting swelling peak timeline and the guide to a bee sting still swollen after three days, exist for exactly the moment this table describes; the companion page on how long bite swelling can last covers the slower end of normal.
At the hospital end, the error is directly counted. Reviewing 259 patients admitted from an emergency department with lower-extremity cellulitis, researchers found 30.5% had been misdiagnosed — the true problem was an inflammatory mimic, grouped as pseudocellulitis (JAMA Dermatology (Weng et al., 2017), 2017). Among the misdiagnosed patients admitted primarily for cellulitis, 92.3% received antibiotics they did not need (JAMA Dermatology (Weng et al., 2017), 2017). Scaled nationally, the authors estimate this single diagnostic confusion drives up to 130,000 unnecessary hospitalizations and up to $515 million in avoidable spending in the United States each year.
| METRIC | VALUE | SOURCE |
|---|---|---|
| Admitted cellulitis patients who were misdiagnosed | 30.5% | JAMA Dermatology (Weng et al., 2017) |
| Patients in the misdiagnosis cohort | 259 | JAMA Dermatology (Weng et al., 2017) |
| Misdiagnosed admissions given unnecessary antibiotics | 92.3% | JAMA Dermatology (Weng et al., 2017) |
| Misdiagnosed admissions that did not require hospital care | 84.6% | JAMA Dermatology (Weng et al., 2017) |
| Estimated unnecessary hospitalizations per year, US (upper) | 130,000 | JAMA Dermatology (Weng et al., 2017) |
| Estimated avoidable spending per year, US (upper) | $515 million | JAMA Dermatology (Weng et al., 2017) |
Scope first, because it disciplines everything else: this cohort is lower-extremity cellulitis at one large urban US hospital, not sting cases, and the national figures are modelled projections built from it, not counts. What transfers to stings is the mechanism, not the exact rate. The misdiagnosed group — ‘pseudocellulitis’ — is made of inflammatory look-alikes, and large local reactions are prominent among them: a current Australian hospital guideline states plainly that large local allergic reactions are frequently misdiagnosed as cellulitis, and StingHelp’s own explainer on bug bite infection, cellulitis and antibiotics walks through the same differential from the bite side, as does the comparison of erythema migrans versus cellulitis. Read together with the clinic-door data, the picture is of one error measured at both ends: reactions prescribed antibiotics they do not need in primary care, and mimics admitted for intravenous treatment they do not need in hospital — with a projected 9,000 hospital-acquired infections a year as part of the collateral cost.
Mostly, reassurance — with one honest argument attached. Natural-history studies, which followed people after a first large local reaction, estimate the risk of a systemic reaction at a future sting at about 4% (Immunity, Inflammation and Disease (Pucci et al., 2019), 2019). Guideline-cited ranges run higher, up to 15%. And one widely reported study claims the risk is roughly 24% — a figure other allergists have disputed in print on methodological grounds, set out below.
| METRIC | VALUE | SOURCE |
|---|---|---|
| Systemic-reaction risk after an LLR, natural-history estimate | 4% | Immunity, Inflammation and Disease (Pucci et al., 2019) |
| Guideline-cited range, upper end | 15% | European Journal of Case Reports in Internal Medicine (Damanti et al., 2016) |
| Rival published claim (disputed) | 24% | Immunity, Inflammation and Disease (Pucci et al., 2019, critiquing Bilò et al., 2019) |
| Same study, patients clearly re-stung by the same insect | 11% | Immunity, Inflammation and Disease (Pucci et al., 2019) |
| Systemic-reaction patients who had a prior LLR | 4.2% | Clinical Case Reports (2025), recounting Pucci et al., Clinical and Molecular Allergy (2015) |
This is the one genuinely contested number on the page, and it is presented as a dispute, not a verdict. The 24% claim comes from a large multicentre study; the rebuttal, published by allergists who ran the earlier natural-history work, argues that patients are unreliable at identifying which insect stung them, and that once the analysis is restricted to patients clearly re-stung by the same insect, the same dataset’s rate falls sharply. Read from the other direction, prior large local reactions are also rare in the histories of people who do react systemically — just 4.2% of systemic-reaction patients in one series had had one. The consensus position a reader can rely on: the risk after a large local reaction is low, it is not zero, and whether to pursue allergy testing or carry epinephrine is a decision to make with an allergist — particularly since a reaction involving breathing, throat or circulation is a different emergency entirely, as the guide to large local reaction versus anaphylaxis explains.
Start from the rule that outranks every statistic here: if a clinician has prescribed you an antibiotic, take it as directed and never stop or skip it on your own. Some sting and bite reactions are genuinely infected, an undertreated skin infection can spread, and no dataset can diagnose the limb in front of you — only an examination can. The figures on this page describe populations, and they cut both ways: they show antibiotics are prescribed very liberally for bites, and they show real infections typically declare themselves at 48 to 72 hours, which is information worth discussing with your prescriber if your own course followed the classic reaction pattern instead.
| METRIC | VALUE | SOURCE |
|---|---|---|
| True secondary infection typically arises by | 72 hours | Nottinghamshire Area Prescribing Committee, Insect Bites and Stings Guidance v1.0 (ratified July 2026) |
| Guideline minimum bite age before antibiotics are considered | 48 hours | Nottinghamshire Area Prescribing Committee, Insect Bites and Stings Guidance v1.0 (ratified July 2026) |
| Bite patients who reattended after a first consultation | 12% | Family Practice (Wilcock et al., 2023) |
What the data on this page legitimately supports is a conversation, and it suggests the questions. What signs of infection did you see? Given that a large local reaction peaks at 24 to 48 hours, what should I expect over the next two days, and what changes should bring me back sooner? Reattendance is a normal part of this pathway — 12% of bite patients in the UK audit returned — so going back with worsening symptoms is the system working, not an inconvenience. The patterns that should always trigger prompt, in-person care are the infection declarations from the timeline section: redness still spreading beyond the first 48 hours, fever, red streaks tracking away from the sting, increasing pain, or pus. And the emergency pattern stands apart from everything on this page: breathing difficulty, throat tightness, widespread hives, dizziness or collapse means epinephrine if available and emergency services immediately, as set out in the anaphylaxis sting warning signs. Diagnosis belongs to the clinician who can examine the limb; this page’s job is to make sure the numbers behind the conversation are real.


This page was built by the Data Gap Method in a degraded run, and the degraded stages are part of the record. Stage one demand mining ran manually through host web search because the Reddit route is blocked from this host. Stage two ran on web search rather than a SERP API. The stage three format filter did not run. Stage four’s existence gate was applied manually against the site’s 681-URL sitemap corpus, which is also the only source of this page’s internal links. Stage six recency ran as a fallback: the sweep script crashed on its Reddit leg (an incomplete-read error, the same host failure as the previous run), so host web searches were used instead; they found no new study inside the thirty-day window that revises any rate used here — the freshest items are a UK prescribing guideline ratified in July 2026 and an Australian hospital guideline updated in August 2026, both resting on the same underlying studies. One verification note: the scripted checker could not reach PubMed from this host, so the ten values taken from the JAMA Dermatology abstract were read verbatim from that abstract through a browser and confirmed against the published text; every other value was verified by the script against its source page. One widely repeated claim — that about a third of bug bites become infected — could not be traced to any primary source and was dropped; a UK evidence review found no published UK rate of bacterial infection after insect bites at all, so this page claims none. No paid API, tool or data source was used at any stage.
Timing is the strongest clue in the data. A large local reaction starts within minutes to hours, keeps swelling for 24–48 hours, then plateaus and fades over several days. A true bacterial infection typically declares itself later — around 48–72 hours after the bite — often after scratching, and tends to keep worsening with increasing pain, spreading redness, red streaks, pus or fever. The two can look identical on day one, which is exactly why misdiagnosis is so common. Only a clinician who examines you can diagnose your case: if redness is spreading, you have a fever, red streaks are tracking away from the sting, or the pain is getting worse rather than better, seek medical care promptly. (Royal Children's Hospital Melbourne, Clinical Practice Guideline: Cellulitis and skin infections (updated August 2026), 2026)
No — never stop or skip a prescribed antibiotic on your own, and nothing on this page is a reason to. Some sting and bite reactions really are infected, and stopping a course early can leave a genuine infection undertreated. What the data on this page supports is a conversation: if your swelling followed the classic reaction timeline (fast onset, peak at 24–48 hours, then easing) and you are unsure why an antibiotic was prescribed, ask the prescriber what signs of infection they saw and what should happen over the next two days. If your symptoms worsen — spreading redness, fever, red streaks, increasing pain — seek medical care promptly rather than waiting. (Nottinghamshire Area Prescribing Committee, Insect Bites and Stings Guidance v1.0 (ratified July 2026), 2026)
Longer than most people expect, which is part of why it gets mistaken for infection. The swelling typically keeps building for the first 24–48 hours, and the reaction can persist for 7 to 10 days before it fully settles. A reaction that is still large on day three but has stopped spreading and is slowly easing fits the reaction pattern; one that is newly worsening after 48–72 hours, with fever, red streaks or pus, fits infection better and needs medical care. (Tropical Medicine and Infectious Disease (2024), 2024)
Common enough that every sting-season clinic sees them, but the published numbers disagree: estimates run from 2.4% of stung people up to 26% in some adult studies, with most adult studies reporting 5–15% and beekeepers — who are stung repeatedly — at 12–38%. The spread is mostly about definitions: studies that require a swelling over 10 cm across lasting more than 24 hours count fewer cases than studies that accept any dramatic swelling. (European Journal of Case Reports in Internal Medicine (Damanti et al., 2016), 2016)
For most people, no. Natural-history studies put the risk of a systemic reaction at a later sting at about 4% after an initial large local reaction, and most people who react largely once keep reacting largely. One widely reported study claimed a risk near 24%, but allergists disputed its methods in print, and its own figure falls to 11% when only patients clearly stung again by the same insect are counted. The risk is low but not zero, so if you have had a large local reaction, discuss testing and whether to carry epinephrine with an allergist — especially if any reaction ever involved your breathing, throat, or circulation, which is an emergency pattern, not a local one. (Immunity, Inflammation and Disease (Pucci et al., 2019), 2019)
Because the two conditions share almost every visible sign, and the signs that most worry clinicians are the ones a large local reaction produces on purpose. In the English out-of-hours data, swelling nearly tripled the odds of an antibiotic prescription (odds ratio 2.88) and signs of spreading more than tripled them (3.45) — yet both are normal features of a big allergic reaction. Add time pressure and the real risk of missing a genuine infection, and a prescription becomes the default: 67.1% of bite-only encounters in that dataset ended with one. (BMJ Open (Finnikin et al., 2023), 2023)
Seek medical care promptly if redness keeps spreading after the first 48 hours, you develop a fever, red streaks track away from the sting, pain is increasing instead of easing, there is pus, or the swelling involves your face, lips, tongue or throat. Call emergency services immediately for trouble breathing, throat tightness, widespread hives, dizziness or collapse — those are signs of anaphylaxis, a different and dangerous reaction. Hospital guidelines list large local allergic reactions among the conditions most frequently misdiagnosed as cellulitis, but they also stress the reverse error exists: real infections do happen after bites, which is why worsening symptoms always deserve an in-person assessment. (Royal Children's Hospital Melbourne, Clinical Practice Guideline: Cellulitis and skin infections (updated August 2026), 2026)
Last updated:
This article is for informational purposes only and isn’t medical advice. If you’re worried about a bite or sting, talk to a healthcare professional.
Dr. Jones oversees StingHelp’s clinical verification process. Every guide is systematically evaluated against active Centers for Disease Control and Prevention (CDC), Environmental Protection Agency (EPA), and American Academy of Allergy, Asthma & Immunology (AAAAI) medical consensus standards to ensure symptom distinctions and care recommendations are clinically sound.
Explore physician-reviewed first-aid procedures, identification clues, and symptom comparisons for other common outdoor bites and stings.

Alpha-Gal Symptoms Hours After Eating Red Meat: Why You Wake Up With Hives at Night The fast answer: If hives, intense itching, or stomach…

Learn why multiple stings need extra caution, how anaphylaxis differs from high venom exposure, which symptoms need emergency care, and what to do first.

Most mosquito bites cause mild itching and swelling. Learn which signs can suggest infection, a serious allergic reaction, or another reason to seek prompt or emergency medical care.