Direct answer: Multiple bee, wasp, hornet, or yellowjacket stings deserve more caution than a single uncomplicated sting. There are two different concerns: allergic reactions, which can occur even after one sting in a sensitized person, and large venom exposure, which becomes more relevant when someone is stung many times. AAD advises seeking medical attention when someone has been stung multiple times, particularly a child.
Call 911 immediately for trouble breathing, throat or tongue swelling, fainting, collapse, severe dizziness, widespread hives with vomiting or breathing symptoms, or other signs of anaphylaxis. If the person has clinician-prescribed epinephrine, use it according to their emergency plan and still seek emergency care.
Allergy and venom toxicity are not the same problem
Anaphylaxis is an immune reaction to venom. It can happen after a single sting and may progress rapidly. The number of stings does not have to be large.
A large venom load is different. Many stings expose the body to more venom and can cause systemic illness even in a person who does not have a classic venom allergy. The risk depends on the insect, number of stings, body size, age, underlying health, and symptoms. There is no single online sting-count threshold that is safe for everyone.
Why children deserve extra caution after multiple stings
A child has less body mass than an adult, so the same number of stings represents a larger venom exposure relative to body size. AAD specifically recommends medical attention when someone is stung multiple times, particularly a child.
If a child has received many stings, appears weak or ill, is vomiting repeatedly, has significant swelling, breathing symptoms, unusual sleepiness, severe pain, or any systemic reaction, seek prompt medical care rather than counting lesions and waiting.
The first priority is getting away from the insects
If bees, wasps, hornets, or yellowjackets are actively attacking, leave the area quickly. Social insects may defend a nest and sting repeatedly. NIOSH advises running away from a group attack and getting indoors or to shelter rather than staying near the source.
Do not stop beside an active nest to treat the first sting. The safest first aid begins after the person is out of the attack zone.
Do not jump into water to escape a swarm
NIOSH warns against jumping into water during an attack because some insects can remain nearby and wait above the surface. Get indoors or into an enclosed vehicle/building when possible.
If a person falls, is injured while escaping, or has another trauma, address that injury as well as the stings.
Honey bee stingers versus wasp and hornet stings
Honey bees commonly leave a barbed stinger in the skin. Remove visible stingers promptly because venom can continue to be delivered while the stinger remains. Wasps, hornets, and yellowjackets generally do not leave the same type of barbed stinger and can sting repeatedly.
If there are many stings, quickly scan exposed skin for retained stingers without delaying emergency care for severe symptoms. Do not spend several minutes searching every skin mark if the person is having breathing difficulty or collapsing.
Immediate first aid after multiple stings
- Get away from the insects and into a safer location.
- Assess breathing, alertness, circulation, and severe allergic symptoms.
- Use prescribed epinephrine immediately if the person’s emergency plan calls for it.
- Call 911 for anaphylaxis, collapse, severe breathing symptoms, or rapid deterioration.
- Remove visible retained honey bee stingers promptly.
- Wash sting sites with soap and water.
- Use cool wrapped compresses for local pain and swelling if the person is stable.
- Remove rings, watches, or tight items early if hands or limbs are swelling.
Symptoms that suggest anaphylaxis
- Difficulty breathing, wheezing, or noisy breathing
- Throat tightness or trouble swallowing
- Swelling of the tongue, lips, face, or mouth
- Fainting, collapse, severe dizziness, or signs of shock
- Widespread hives with vomiting, breathing symptoms, or dizziness
- Rapidly progressive symptoms involving more than the local sting sites
Anaphylaxis is an emergency. Antihistamines do not replace epinephrine when epinephrine is indicated.
Symptoms after many stings that need medical evaluation even without classic allergy
Seek prompt medical attention when someone has many stings or develops repeated vomiting, severe weakness, marked headache, chest symptoms, significant abdominal symptoms, confusion, faintness, dark urine, decreased urination, widespread swelling, or other systemic illness.
MedlinePlus notes that bee, wasp, hornet, and yellowjacket venom can cause systemic effects and that serious reactions may require emergency evaluation and hospital monitoring.
Why exact sting counts can be misleading

People often search for a number such as “How many stings are dangerous?” A fixed number can create false reassurance. Ten stings in a small child, dozens of stings in an adult with heart disease, and one sting in a person with severe venom allergy are very different situations.
Instead of relying on a universal cutoff, consider age and body size, known allergy history, insect type, number of stings, location of stings, symptoms, and how quickly the person’s condition is changing.
Stings in the mouth or throat
A sting inside the mouth, tongue, or throat deserves urgent assessment because local swelling can threaten the airway even without a generalized allergic reaction. MedlinePlus advises emergency evaluation for stings in the mouth or throat.
Do not give food or drink to someone who is having trouble swallowing or breathing.
Stings near the eye
Swelling around the eye can become dramatic. Seek prompt care when the eyeball itself may have been stung, vision changes, eye movement is painful, there is significant eye pain, or swelling prevents normal eye function.
Do not apply household chemicals, vinegar, baking soda, or other irritants near the eye.
Large local reactions after several stings
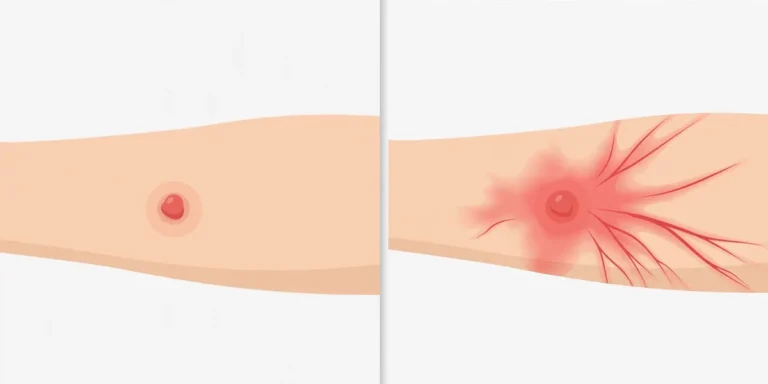
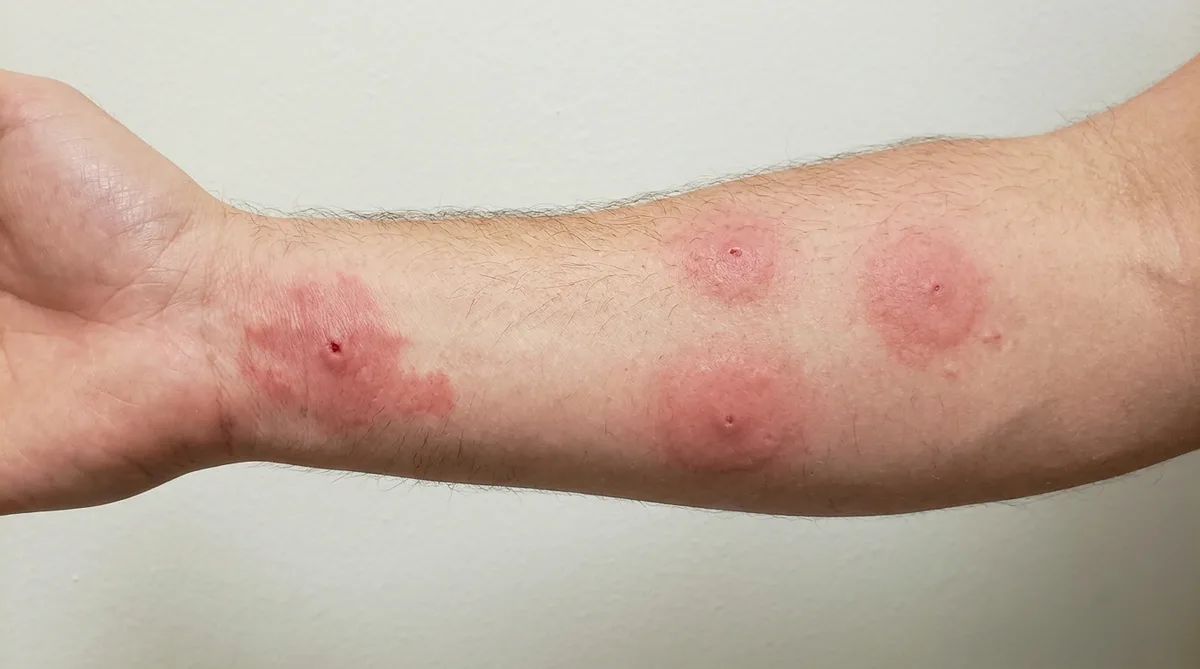
Multiple stings can produce several overlapping areas of redness and swelling. A large local reaction is not automatically anaphylaxis. The distinction depends on whether symptoms remain local or involve breathing, circulation, generalized hives, gastrointestinal symptoms, or other systemic signs.
Even when symptoms are local, a large number of stings can justify medical assessment because total venom exposure matters.
When swelling becomes an infection concern
Venom inflammation can cause warmth, redness, and tenderness for a period after the event. Bacterial infection becomes more concerning when pain is steadily worsening, redness continues expanding with increasing tenderness, drainage or pus develops, red streaks appear, fever occurs, or the person becomes increasingly unwell.
Do not start leftover antibiotics. See StingHelp’s bite/sting infection and cellulitis guide for the difference between inflammation and bacterial infection.
People with known sting allergy
A person with a history of anaphylaxis to insect venom should follow the emergency plan provided by their allergy clinician and carry prescribed epinephrine as directed. After using epinephrine, emergency evaluation is still important because symptoms can persist or recur.
After recovery, discuss prevention and allergy follow-up with a qualified clinician. Venom immunotherapy may be considered for some people with serious sting allergy; that decision belongs with an allergy specialist.
What to tell 911, Poison Control, or the emergency department
- Age and approximate weight
- Known insect if identified
- Estimated number of stings
- Time of the attack
- Location of stings, especially mouth, throat, or eye
- Breathing, fainting, vomiting, chest, neurologic, or urinary symptoms
- Known venom allergy and whether epinephrine was used
- Major heart, lung, kidney, or immune conditions
- Current medications
Poison Control can help in the United States
For questions about significant venom exposure when the person is not already in a life-threatening emergency, U.S. Poison Control can provide individualized guidance. If there are severe symptoms, call 911 first rather than delaying emergency care.
How to prevent repeat multiple-sting events
- Do not disturb bee, wasp, hornet, or yellowjacket nests.
- Inspect work areas, eaves, shrubs, trees, sheds, and ground holes before high-risk tasks.
- Keep outdoor trash covered and food spills cleaned.
- Wear closed shoes during yard work.
- Teach children not to throw objects at nests or insect colonies.
- Use professional pest management when a nest creates repeated exposure near a home, school, workplace, or high-traffic area.
Workplace multiple-sting events
Outdoor workers should have a plan for stinging-insect incidents. The plan should cover escape routes, how to call emergency services, who will stay with the worker, where first-aid supplies are stored, and how a known allergic worker’s prescribed emergency medication is handled.
See StingHelp’s outdoor-worker bite and sting prevention guide for a worksite checklist.
Common mistakes after many stings
- Staying near the nest to count or photograph insects.
- Assuming no allergy because previous stings were mild.
- Waiting for hives before taking breathing difficulty seriously.
- Relying on an exact “dangerous number” of stings.
- Using antihistamines instead of epinephrine during anaphylaxis.
- Ignoring systemic illness because each sting site looks small.
- Driving alone during a severe reaction.
Frequently asked questions
Can one sting cause anaphylaxis?
Yes. A severe allergic reaction can occur after a single sting in a sensitized person.
Can many stings be dangerous without an allergy?
Yes. A large venom exposure can cause systemic illness even without classic IgE-mediated anaphylaxis.
Should every person with several stings go to the ER?
The safest level of care depends on the number of stings, age/body size, symptoms, sting location, allergy history, and health conditions. AAD advises medical attention for multiple stings, particularly in children. Emergency symptoms require 911.
Should I remove every bee stinger before calling for help?
Remove visible retained stingers promptly when it does not delay emergency treatment. Airway, breathing, circulation, and epinephrine for anaphylaxis take priority.
Related StingHelp guides
- Emergency warning signs after bites and stings
- Bite and sting first aid
- Bee sting vs wasp sting
- Infection and cellulitis after bites/stings
Authoritative sources
- American Academy of Dermatology: How to Treat a Bee Sting
- American Academy of Dermatology: When Bites and Stings Need Care
- MedlinePlus: Bee, Wasp, Hornet, or Yellow Jacket Sting
- CDC/NIOSH: Insects and Scorpions at Work
Bottom line
Multiple stings require more caution because allergy risk and total venom exposure are separate concerns. Get away from the insects, assess for anaphylaxis, use prescribed epinephrine when indicated, call 911 for severe symptoms, and seek medical advice after multiple stings—especially in a child or when systemic symptoms develop.
Educational information only; this guide does not provide a universal safe sting count or replace emergency medical evaluation.
Observation after the first emergency symptoms improve
A person treated for a severe allergic reaction may need continued medical observation because symptoms can recur after initial improvement. Follow the emergency clinician’s instructions rather than assuming that feeling better after epinephrine means the episode is completely over. Do not send the person back to strenuous work, driving, or an isolated setting until the treating team says it is appropriate.
Older adults and people with chronic medical conditions

Heart disease, lung disease, kidney disease, frailty, and medications can affect how well someone tolerates a large sting event or severe allergic reaction. A lower threshold for medical assessment is reasonable when many stings occur in a medically vulnerable person, even if the skin findings look ordinary.
Why hydration and urine changes can matter after a large sting burden
After a very large venom exposure, emergency clinicians may monitor kidney function, muscle injury, blood counts, and other laboratory measures. At home, reduced urination, very dark urine, severe weakness, repeated vomiting, confusion, or worsening systemic symptoms are reasons to seek urgent medical care rather than treating the event as a routine local reaction.
Do not return to the nest to identify the species
Identification can be useful, but it is not worth another attack. A distant photograph of the nest or insect taken only when safe may help later. If the colony is in a high-traffic location, use trained pest-management professionals. The medical team can treat severe allergy or venom effects even when the exact species remains uncertain.
After recovery: allergy evaluation can prevent future emergencies
Someone who experienced a systemic allergic reaction to a bee, wasp, hornet, or yellowjacket sting should discuss follow-up with a qualified clinician. An allergy specialist can assess whether venom testing, a prescribed epinephrine plan, and venom immunotherapy are appropriate. This is different from simply treating the local swelling after the event.
School, camp, and workplace planning after a severe reaction
When a child, camper, or employee has a known severe venom allergy, the relevant adults should know the emergency plan and how to access prescribed epinephrine according to local policies. Emergency contact information should be current, and activities near known nests should be modified when practical. The goal is not to eliminate all outdoor activity but to make the response predictable if another sting occurs.
Multiple stings and pregnancy
Pregnant people with multiple stings or systemic symptoms should seek medical advice promptly. Emergency treatment of anaphylaxis should not be delayed because of pregnancy. The treating team can balance maternal and fetal considerations while addressing the immediate threat.
What not to apply to dozens of sting sites
Avoid coating large areas of skin with vinegar, baking soda, bleach, essential oils, meat tenderizer, or other household remedies. These approaches do not remove injected venom and can irritate already-injured skin. Basic washing, cool compresses, and clinician-directed symptom treatment are safer while the person is monitored for systemic effects.
Follow-up questions to ask after a significant event
- Was this an allergic reaction, a high venom exposure, or both?
- Should I carry epinephrine?
- Do I need an allergy referral?
- What symptoms would require emergency care after a future sting?
- Are there work, school, travel, or outdoor-activity precautions I should add?
- Should the nest or exposure site be professionally managed?