Direct answer: An insect bite or sting does not automatically mean you need a tetanus booster. The decision depends on the type of skin wound and your tetanus vaccination history. CDC classifies clean, minor wounds differently from dirty or major wounds such as puncture wounds or wounds contaminated with soil or devitalized tissue. If you completed the primary tetanus series and your last tetanus-containing vaccine was less than 5 years ago, CDC says no tetanus vaccination is needed for any wound type.
For a clean, minor wound, a booster is generally considered when the last tetanus vaccine was 10 or more years ago. For a dirty or major wound, the interval is shorter: a booster is generally recommended when the last tetanus vaccine was 5 or more years ago. People with an unknown, incomplete, or absent primary vaccination series need medical guidance for any wound.
Why this question comes up after bites and stings
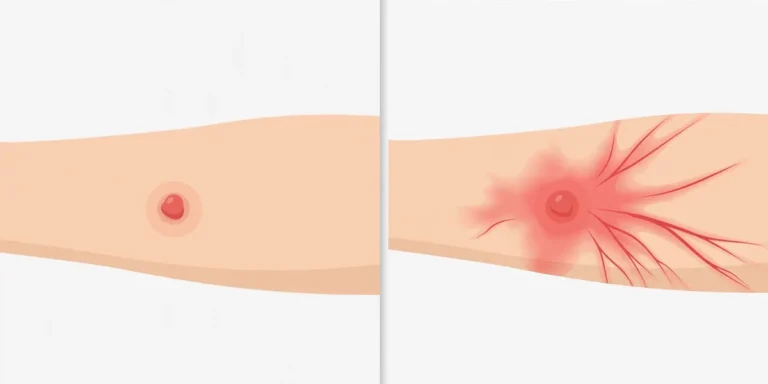
Most mosquito bites, uncomplicated bee or wasp stings, flea bites, and similar superficial skin reactions do not behave like deep contaminated puncture wounds. They may itch, swell, or become tender, but tetanus prevention is based on wound characteristics and vaccination history—not on the fact that an insect was involved.
The situation deserves more attention when the skin injury is deep, puncture-like, contaminated with soil, contains foreign material, includes damaged or dead tissue, or occurred together with another injury. For example, someone stung while gardening might also have a puncture or cut contaminated with soil. That accompanying wound can matter more for tetanus risk than the sting itself.
CDC wound categories: clean/minor versus dirty/major
CDC separates wounds into broad risk groups. Clean and minor wounds are lower risk. Dirty or major wounds carry more risk because they can create conditions in which Clostridium tetani spores can grow.
Examples CDC gives for dirty or major wounds include penetrating or puncture wounds; wounds contaminated with dirt, soil, feces, or saliva; burns; crush injuries; compound fractures; frostbite; and wounds with necrotic or gangrenous tissue. An ordinary itchy insect bump is not automatically placed in this higher-risk category.
| Situation | Typical tetanus question | What matters most |
|---|---|---|
| Superficial mosquito or flea bite | Usually not a tetanus-specific emergency | Vaccination history, skin integrity, signs of infection |
| Routine bee/wasp sting | Usually managed as a sting unless another wound exists | Allergy symptoms, local care, vaccination status if there is a true wound |
| Deep puncture or contaminated cut during insect exposure | Higher tetanus relevance | Depth, contamination, last tetanus dose, primary series |
| Unknown vaccine history | Needs professional vaccination review | Whether the primary series was ever completed |
When CDC says a tetanus vaccine is not needed
CDC states that no tetanus vaccination is needed—regardless of wound type—when a person has completed the primary vaccine series and received the most recent tetanus vaccine less than 5 years ago. This is one reason it is useful to know approximately when your last Tdap or Td dose was given.
If you are unsure, check your medical portal, pharmacy records, state immunization registry, primary-care records, school or employment records, or ask a clinician. Do not guess a vaccination date if a real record can be found.
Clean minor wounds: the 10-year interval
For people who completed the primary tetanus series, CDC recommends tetanus vaccination for a clean, minor wound when the last tetanus vaccine was 10 or more years ago. This follows the routine booster interval used for adults.
A clean minor wound should still be cleaned and monitored. Tetanus is not the only concern after broken skin; irritation and ordinary bacterial infection can also occur.
Dirty or major wounds: the 5-year interval
For a dirty or major wound, CDC recommends tetanus vaccination when a fully vaccinated person’s last tetanus-containing vaccine was 5 or more years ago. The shorter interval reflects the increased risk associated with contaminated, puncture, or devitalized wounds.
If an insect encounter happened at the same time as a deeper injury—for example, a person fell onto a rusty or dirty object while reacting to a wasp nest—describe the actual wound to the clinician. “I was stung” does not capture a separate puncture or contaminated laceration.
What if you never completed the tetanus vaccine series?
CDC recommends vaccination for all wounds when a person’s tetanus vaccination history is unknown, when they are unvaccinated, or when they have not completed the primary series. The exact vaccine product and schedule depend on age, previous doses, and other factors.
Some higher-risk dirty or major wounds may also require tetanus immune globulin (TIG) in people who are unvaccinated, incompletely vaccinated, have unknown vaccination history, or have certain severe immune conditions. TIG is not used for clean, minor wounds.
This is a clinician decision. Do not try to substitute an extra antibiotic or topical product for appropriate vaccination assessment.
Antibiotics do not prevent tetanus after a wound
CDC specifically advises against using topical or systemic antibiotics simply to prevent tetanus after a wound. Tetanus prevention relies on appropriate wound care, vaccination, and—when indicated—TIG. Antibiotics may be used when there is an actual bacterial wound infection, but that is a different clinical problem.
Using leftover antibiotics “just in case” can expose a person to side effects and contribute to inappropriate antibiotic use without solving the tetanus question.
What to do immediately after a bite or sting that breaks the skin
- Move away from the insect source if there is risk of additional stings or bites.
- Wash the skin gently with soap and clean water.
- Remove visible dirt or foreign material from a wound when it can be done safely.
- For a retained bee stinger, remove it promptly rather than leaving it in the skin.
- For an attached tick, use clean fine-tipped tweezers and steady upward pressure.
- Do not cut, burn, suction, or pour caustic chemicals into the skin.
- Check your tetanus vaccination history if the injury is more than a superficial skin reaction.
Tetanus risk is different from an allergic emergency
A severe sting allergy can become life-threatening within minutes and has nothing to do with whether a tetanus booster is due. Call 911 for trouble breathing, throat or tongue swelling, fainting, collapse, severe dizziness, or a rapidly progressive generalized allergic reaction. If a person has clinician-prescribed epinephrine, use it according to the emergency plan.
Do not delay emergency treatment while trying to locate vaccination records.
Tetanus risk is also different from skin infection
A bite or sting can become secondarily infected, especially after scratching. Increasing pain, warmth, tenderness, drainage, red streaking, fever, or rapidly worsening redness can justify medical evaluation. These signs do not tell you whether a tetanus booster is due; vaccination history and wound type still determine that question.
See StingHelp’s infection, complications, and healing guide for practical signs that distinguish routine inflammation from a problem that deserves assessment.
Children: check the vaccine record rather than using adult rules from memory
Children receive tetanus-containing vaccines on an age-based schedule. A parent should use the child’s immunization record and pediatric guidance rather than assuming the adult 10-year booster rule applies in the same way. If a child’s wound is deep, contaminated, or the vaccine history is incomplete or uncertain, contact the pediatrician or urgent-care clinician.
Pregnancy and Tdap
Pregnancy has its own Tdap recommendations, including vaccination during each pregnancy. A wound-related tetanus decision should be discussed with the obstetric or medical team because the person’s current pregnancy vaccination plan and prior doses matter. Do not skip emergency wound care while waiting for a routine prenatal visit.
When to contact a clinician the same day
- The wound is deep, puncture-like, heavily contaminated, crushed, burned, or contains dead tissue.
- You do not know when your last tetanus-containing vaccine was given.
- You never completed the primary tetanus series.
- The wound cannot be cleaned adequately at home.
- There is a retained foreign body.
- Increasing pain, drainage, fever, red streaking, or other infection signs develop.
- The injury involves the eye, mouth, hand function, or another sensitive area.
When emergency care matters more than a booster question
Call emergency services for severe allergic symptoms, collapse, major bleeding, severe trauma, airway swelling, serious neurologic symptoms, or rapid deterioration. The tetanus decision can be addressed after immediate threats are stabilized.
Common mistakes to avoid
- Assuming every insect bite needs a tetanus shot. Wound type and vaccine history matter.
- Assuming “rust” itself causes tetanus. The concern is wound contamination and conditions that allow tetanus spores to grow, not rust color.
- Using antibiotics as tetanus prevention. CDC does not recommend this.
- Ignoring a separate puncture or dirty wound because an insect sting happened at the same time.
- Waiting for symptoms of tetanus before checking vaccination. Prevention decisions are made before disease develops.
A practical checklist before you call
Have the following information ready: your age; when the injury happened; whether it is superficial, puncture-like, dirty, crushed, burned, or otherwise significant; what contaminated the wound; when your last Tdap or Td was given; whether you completed the primary vaccine series; major immune conditions; and any current signs of infection or severe allergic reaction.
Related StingHelp guides
- Bite and sting first aid
- Emergency warning signs
- Infection, complications, and healing
- How to clean a bite or sting safely
Authoritative sources
- CDC: Clinical Guidance for Wound Management to Prevent Tetanus
- CDC: Clinical Care of Tetanus
- MedlinePlus: Insect bites and stings
Bottom line
An insect bite or sting does not create an automatic tetanus-booster rule. Check the actual wound and your vaccination history. A person who completed the primary series and had a tetanus vaccine within the past 5 years generally does not need another dose for a wound. Clean minor wounds use a 10-year interval; dirty or major wounds use a 5-year interval. Unknown or incomplete vaccination history needs professional review.
This article provides general educational information for a U.S. audience. It does not diagnose a wound or replace individualized vaccination advice.
Examples: how the tetanus decision changes with the wound
Example 1: itchy mosquito bump, skin intact. A person notices an itchy welt after sitting outside. There is no puncture wound beyond the expected superficial bite, no soil contamination, and the person is otherwise well. The main issues are itch relief and monitoring; this does not create an automatic tetanus-booster indication.
Example 2: bee sting while gardening plus a dirty nail puncture. The bee sting and the puncture should be considered separately. The sting raises allergy and local-reaction questions; the contaminated puncture raises the tetanus question. If the last tetanus-containing vaccine was 5 or more years ago and the puncture qualifies as a dirty/major wound, CDC guidance supports vaccination review.
Example 3: unknown vaccine history after a deeper wound. Do not try to reconstruct the schedule from memory if records are unavailable. CDC recommends vaccination assessment for people with unknown vaccination history for all wounds, and some dirty or major wounds can also require TIG.
Example 4: fully vaccinated adult with a recent Tdap. If the primary series is complete and the last tetanus-containing vaccine was less than 5 years ago, CDC says another tetanus vaccine is not needed for wound management, regardless of wound type.
Does a tick bite require a tetanus shot?
An attached tick does not automatically mean a tetanus booster is needed. Remove the tick promptly, clean the site, and evaluate tetanus vaccination based on the actual wound and vaccination history. Tickborne disease monitoring is a separate issue. Fever, rash, severe headache, neurologic symptoms, or other significant illness after a tick exposure should be discussed with a healthcare professional even when the tetanus vaccine is current.
Does a bee, wasp, or hornet sting require a tetanus shot?
Most routine stings are managed for pain, swelling, retained stinger when present, and allergic symptoms. A tetanus booster is not automatically required because venom was injected. If the sting occurred together with a dirty puncture, laceration, fall, or other significant skin injury, evaluate that wound separately using CDC guidance.
Does scratching a bite change tetanus risk?
Scratching can break the skin and increase the chance of ordinary bacterial infection, but a scratched mosquito bite is not automatically equivalent to a high-risk tetanus wound. Clean the area, reduce scratching, and watch for infection. If scratching produces a deeper contaminated wound or you are uncertain about vaccination status, ask a clinician.
Frequently asked questions
Is Tdap the same as a tetanus booster?
Tdap contains protection against tetanus, diphtheria, and pertussis. Td protects against tetanus and diphtheria. Which product is appropriate depends on age, prior vaccination, pregnancy, and current recommendations.
Can I wait until a wound looks infected before checking tetanus status?
No. Tetanus prevention is based on vaccination history and wound assessment, not on waiting for infection signs. A wound can need vaccination review even before any redness or drainage develops.
Can urgent care give a tetanus booster?
Urgent-care clinics, primary-care offices, pharmacies, and emergency departments commonly assess tetanus vaccination needs, but availability and age rules vary by location. Bring any vaccine record you can access.
What if I received Tdap during a recent pregnancy?
That dose counts as a tetanus-containing vaccine. Tell the clinician the date it was given so wound-management guidance can be applied accurately.