
Bed Bug Bites vs Eczema: How to Tell Apart
You wake up with itchy red marks, and the internet offers two suspects: bed bugs or eczema. The question of bed bug bites vs…
Compare lone star tick bites and no-see-um bites by attachment, bite pattern, habitat, alpha-gal risk, tick-borne illness, first aid, and warning signs.

Bottom line: A lone star tick exposure and a no-see-um exposure usually tell two very different stories. A lone star tick can attach to the skin and feed for hours or longer; the medically important issues include tick-borne infections and, in some people, development of alpha-gal syndrome after a tick bite. No-see-ums are tiny flying biting midges that usually produce multiple itchy bites on exposed skin during a short outdoor exposure, especially around wetlands, coastlines, and other humid environments.

The skin appearance comes after those questions because red bumps are nonspecific. Many insect bites, allergic reactions, scratched lesions, and minor infections look similar in a photograph.
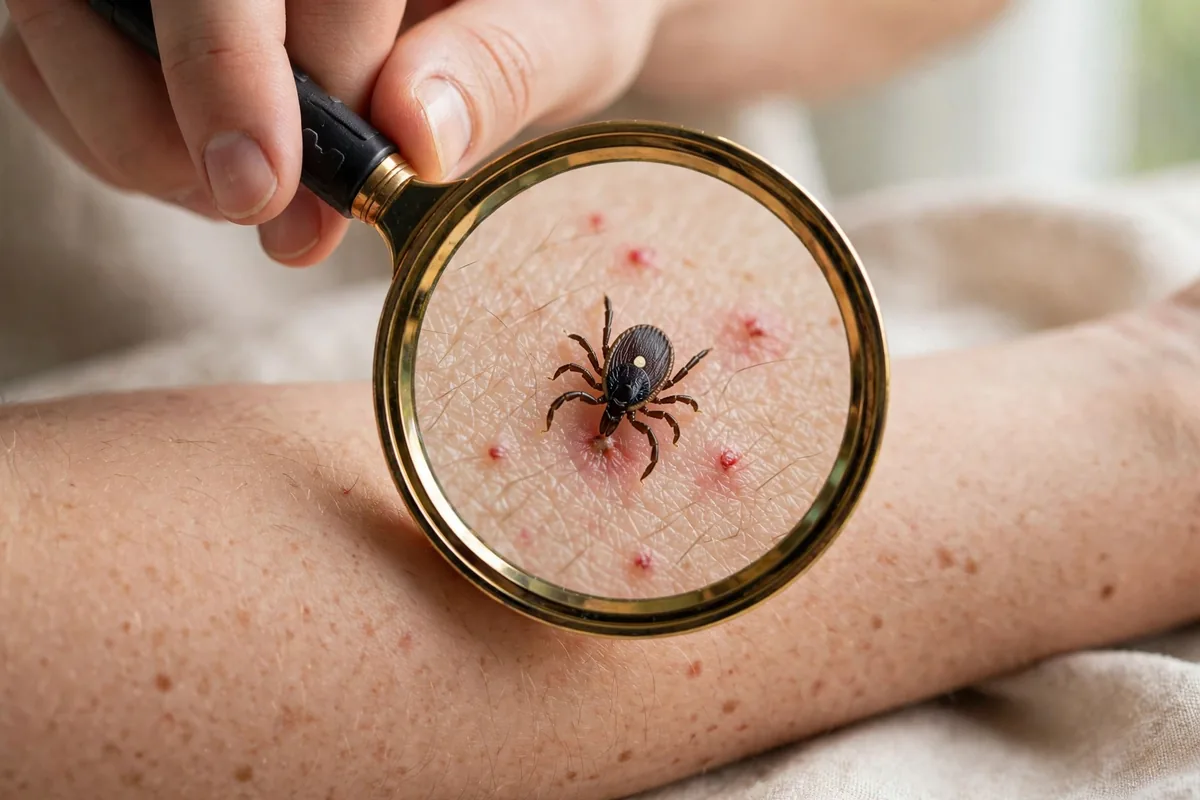
The lone star tick, Amblyomma americanum, is an aggressive human-biting tick found widely in the eastern, southeastern, and south-central United States. Adult females have a noticeable pale or white dot on the back, while nymphs are much smaller and do not show the same obvious marking.
A tick does not need to look large to matter. Nymphs can be difficult to notice. If a tick is attached, remove it promptly rather than waiting for the skin to become irritated.
No-see-ums are tiny biting midges. They are flying insects, not ticks or mites. University of Florida IFAS Extension notes that many are around 1 millimeter long, making them difficult to see and small enough to pass through ordinary screening.
They are often encountered around coastal marshes, mangroves, estuaries, beaches, ponds, lakes, damp soil, and humid vegetation. One person can receive many bites within a short time, especially at dawn, dusk, or during calm humid conditions.

| Pattern | Lone star tick | No-see-um |
|---|---|---|
| Contact with skin | Attaches and feeds | Bites quickly and flies away |
| Typical number of lesions | Often one or a few | Frequently numerous |
| Where bites may occur | Exposed or covered skin; hidden folds are common | Mostly uncovered skin |
| Immediate sensation | May be unnoticed | May sting, burn, or itch |
| Later concern | Tick-borne illness or alpha-gal syndrome in susceptible people | Persistent itch, large local reactions, skin infection from scratching |
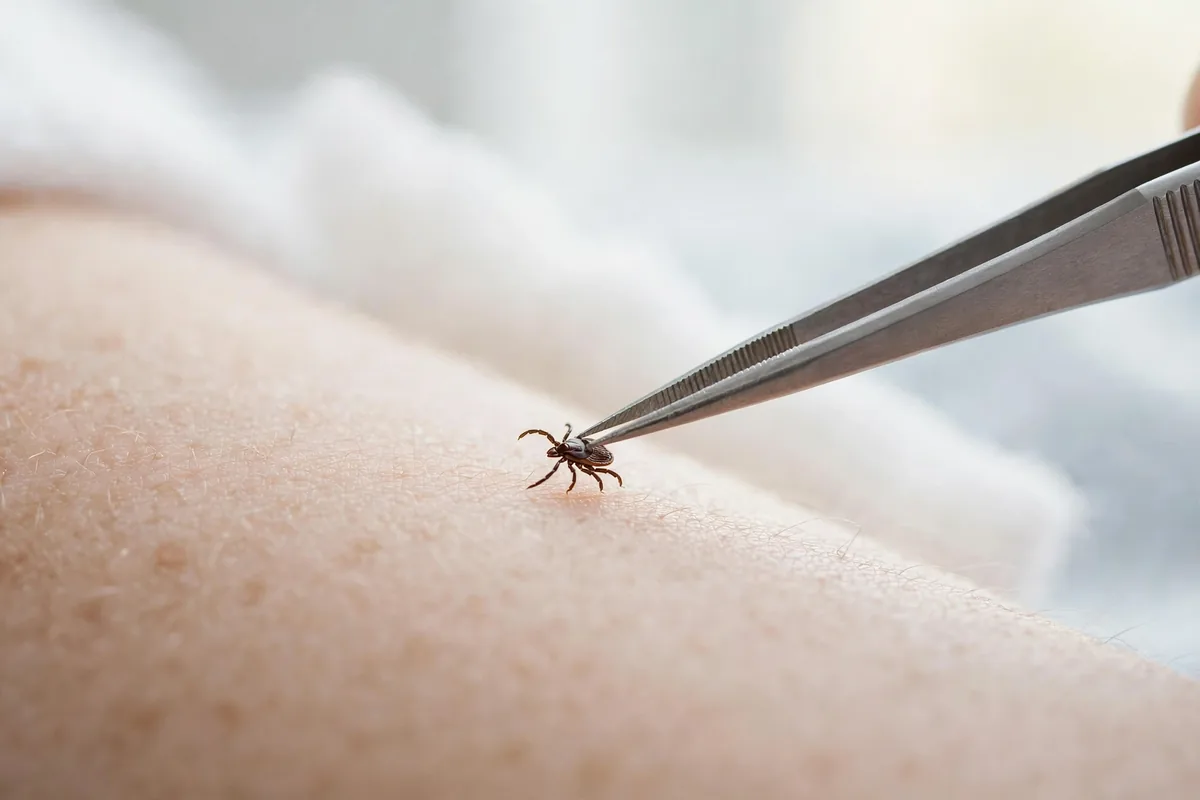
CDC recommends prompt removal with clean fine-tipped tweezers. Grasp the tick close to the skin and pull upward with steady pressure. Do not wait until you know the exact species before removing it.
After removal, clean the skin and your hands. Take a clear photo if possible and note the date, county or state, activity, and likely duration of attachment. These details can be useful if symptoms develop later.
Lone star ticks are not the primary vector for Lyme disease. Their health significance includes other conditions. CDC information links lone star ticks with ehrlichiosis transmission, and lone star tick bites have also been associated with alpha-gal syndrome.
This distinction matters because searching only for a Lyme “bull’s-eye” can create false reassurance. A person may have a medically important lone star tick exposure without ever developing a classic target-shaped rash.
Alpha-gal syndrome is an allergy to the sugar molecule alpha-gal. CDC states that in the United States, lone star tick bites are most often associated with this condition. Symptoms can occur after eating mammalian meat or other products containing alpha-gal, and the reaction may be delayed by several hours.
Possible symptoms include hives, swelling, gastrointestinal symptoms, breathing difficulty, or anaphylaxis. Not every lone star tick bite causes alpha-gal syndrome, and the syndrome cannot be diagnosed from the bite mark. A clinician or allergist can evaluate a suspicious pattern.
Imagine spending an evening near a salt marsh and noticing repeated tiny stings around the ankles and forearms. The next morning there are many small red itchy bumps on exposed skin. No tick is attached and no single lesion stands out. That history strongly favors biting midges.
No-see-um reactions can be intense, especially in people who are sensitive to the bites. The itch may outlast the actual exposure. The insects are not living beneath the skin.
Lone star ticks can crawl beneath clothing before attaching. Check the scalp, behind ears, armpits, waistline, groin, behind the knees, and other protected areas after outdoor activity.
No-see-ums usually target skin they can reach quickly. Ankles, lower legs, arms, face, and neck are common. Clothing can reduce access, although very loose garments may still allow insects underneath.
Inflammation can form rings, halos, or irregular borders around many bites. A ring around a no-see-um bite does not make it a tick bite. Likewise, a small red spot after removing a lone star tick does not by itself identify a specific infection.
The trend matters: expanding redness plus fever or systemic illness after a tick exposure deserves clinical assessment. A cluster of stable itchy papules after a brief midge exposure is a different pattern.
Contact a healthcare professional if you develop fever, severe headache, unusual fatigue, muscle aches, gastrointestinal symptoms, confusion, or a new rash after a recent tick exposure. Ehrlichiosis can become serious, and early symptoms may resemble other infections.
Also discuss delayed allergic reactions after mammalian meat or dairy-containing products if those symptoms began after tick exposure. Emergency symptoms such as breathing difficulty, throat swelling, fainting, or collapse require immediate care.
Most reactions are local. Seek medical advice when swelling is unusually severe, the rash is not improving, you develop fever after international travel, or scratched bites show signs of infection.
Increasing pain, heat, pus, drainage, spreading redness, or fever can suggest secondary bacterial infection. The original bites may be tiny, but scratching can significantly damage the skin barrier.
In the United States, no-see-ums are usually nuisance biters. Some biting midges can transmit pathogens in other regions of the world. If illness follows travel, tell the clinician the country, region, dates, and type of insect exposure.
Do not use a U.S.-based “no-see-um” assumption to dismiss fever or systemic illness after international travel.
For children, pregnancy, chronic illness, or medication interactions, ask a pharmacist or healthcare professional if you are unsure what is safe.
Do not cut the skin, use suction devices, apply bleach or gasoline, burn an attached tick, or cover bites with harsh chemicals. These approaches can injure the skin without improving the underlying exposure.
For an attached tick, prompt mechanical removal is the priority. For no-see-um bites, gentle skin care and itch control are more useful than trying to “extract” something from the lesion.
A humid wooded coastal trail could expose you to both ticks and biting midges. That is why habitat alone is not enough. The behavior of the arthropod is still the stronger clue.
If you walk through brush near a marsh, perform a tick check even if you were also being bitten by tiny flying insects. One exposure does not rule out the other.
That is a tick exposure. Remove it promptly and monitor for later symptoms.
Biting midges are more plausible, particularly if no tick was found.
Seek medical evaluation and mention the tick exposure. Do not assume it is a routine bite reaction.
This pattern deserves urgent medical evaluation and discussion of alpha-gal syndrome. Emergency symptoms require emergency care.

For a tick, photograph the actual arthropod from above if you can do so safely after removal. For no-see-um exposure, a photo of the rash can document progression, but the insect itself may be too small to identify in a casual phone image.
Include a size reference near the skin and keep lighting consistent. Do not rely on image-search matching as a diagnosis.
If no arthropod was seen, there may be other explanations. Fleas, mosquitoes, chiggers, contact dermatitis, bed bugs, folliculitis, and many skin conditions can mimic insect bites.
Reconsider the diagnosis if lesions keep appearing without new outdoor exposure, symptoms last much longer than expected, or the pattern becomes painful rather than itchy.
Adult female lone star ticks have the familiar pale spot that inspired the common name, but immature ticks are much smaller and harder to identify. A blurry phone photo of a tiny nymph may not be enough to determine species. If the tick is available, save a clear photograph after removal and focus medical follow-up on the exposure and symptoms rather than waiting for perfect species identification.
Species can still matter because different ticks carry different risks. A clinician may use geography, season, attachment history, and the tick’s appearance together when deciding what conditions belong in the differential.
If you suspect alpha-gal syndrome, write down the food eaten, the time it was eaten, when symptoms started, and exactly what happened. Delayed hives, swelling, gastrointestinal symptoms, or breathing problems after mammalian products are more useful to an allergist than simply saying “I reacted to meat.” Emergency symptoms should be treated urgently rather than waiting for an outpatient allergy appointment.
No-see-ums are not the recognized U.S. exposure associated with alpha-gal syndrome. CDC identifies lone star tick bites as the U.S. tick exposure most often associated with it.
Lone star ticks are not considered the primary U.S. vector for Lyme disease. They are associated with other health concerns, including ehrlichiosis and alpha-gal syndrome.
No. They bite briefly and fly away.
No. Many tick bites do not result in infection or allergy. Monitor for symptoms and seek medical advice when appropriate.
No. The exposure history, actual arthropod, lesion number, timing, and body distribution are more useful than a photo alone.
Educational information only. StingHelp does not diagnose tick-borne disease, alpha-gal syndrome, or an insect bite from a photograph. Seek medical care for significant, systemic, persistent, infected, or worsening symptoms.
Dr. Jones oversees StingHelp’s clinical verification process. Every guide is systematically evaluated against active Centers for Disease Control and Prevention (CDC), Environmental Protection Agency (EPA), and American Academy of Allergy, Asthma & Immunology (AAAAI) medical consensus standards to ensure symptom distinctions and care recommendations are clinically sound.
Explore physician-reviewed first-aid procedures, identification clues, and symptom comparisons for other common outdoor bites and stings.
You wake up with itchy red marks, and the internet offers two suspects: bed bugs or eczema. The question of bed bug bites vs…

Your child wakes up covered in itchy red spots and the questions start immediately: is this chickenpox vs bug bites, an allergic reaction, or…

Your child comes in from the yard clutching a caterpillar they thought looked cool, and now their hand is burning. Or you brush a…