
Do Wasp Stings Leave a Stinger? Myth vs Facts
You have just been stung, and your first instinct is to look for the stinger. Do wasp stings leave a stinger? No, they do…
For a honey bee sting, move away from the area, remove a visible stinger promptly, wash the site, and use a wrapped cool compress. Most reactions stay local. Call 911 for breathing difficulty, throat or tongue swelling, fainting, or rapidly worsening whole-body symptoms. A large local reaction is uncomfortable but is not the same as anaphylaxis.

Direct answer: For a honey bee sting, move away from the area, remove a visible stinger promptly, wash the site, and use a wrapped cool compress. Most reactions stay local. Call 911 for breathing difficulty, throat or tongue swelling, fainting, or rapidly worsening whole-body symptoms. A large local reaction is uncomfortable but is not the same as anaphylaxis.
Honey bees are unusual among common stinging insects because a worker honey bee may leave its barbed stinger and venom sac in human skin. That detail changes the first-aid priority: if a stinger is clearly present, remove it promptly. The exact removal method matters less than avoiding delay. The rest of care depends on symptoms, not on how dramatic the redness looks.
A witnessed sting with immediate sharp pain plus a retained stinger strongly supports honey bee exposure. Wasps, hornets, and bumblebees can sting without usually leaving a stinger. Honey bee workers typically sting once because the barbed apparatus can remain in mammalian skin, while the insect flies away. That does not mean every visible puncture contains a stinger, so do not dig into the skin if nothing is clearly present.
A honey bee sting can produce pain, redness, warmth, itching, and swelling. Some people develop a large local reaction that expands for many hours and can involve much of a hand, forearm, foot, or lower leg. Skin appearance alone cannot determine allergy severity. Systemic symptoms such as breathing difficulty, faintness, generalized hives, or tongue swelling matter far more than the diameter of local redness.
For an uncomplicated local sting, cooling the area, elevating a swollen limb, and avoiding friction can help. A pharmacist may recommend an oral antihistamine for itch or an age-appropriate pain reliever when suitable. Hydrocortisone or another topical product may be reasonable for intact skin when label directions allow, but severe pain, rapidly progressive swelling, or systemic symptoms should not be managed by repeatedly adding creams.
Over-the-counter medicines are not appropriate for everyone. Age, pregnancy, kidney or liver disease, glaucoma, prostate problems, medication interactions, and allergy history can change what is safe. Follow the product label and ask a pharmacist or clinician when there is uncertainty.
Pain is often strongest early and then improves. Swelling and itching can increase over the first day and may take several days to settle. A large local reaction can peak later than the initial pain. The trend should gradually move toward improvement rather than progressive illness.
Seek prompt assessment for multiple stings, a sting in the mouth or throat, severe pain that is not settling, vomiting, dizziness, widespread hives, rapidly increasing swelling that compromises function, or signs of infection. A person with a known venom allergy should follow their clinician-provided action plan.
Call emergency services for trouble breathing, throat tightness, wheezing, fainting, severe weakness, confusion, rapidly developing swelling of the tongue or face, or widespread hives accompanied by vomiting, dizziness, or breathing symptoms. If the person has prescribed epinephrine and an established emergency plan, follow that plan and still seek emergency care.
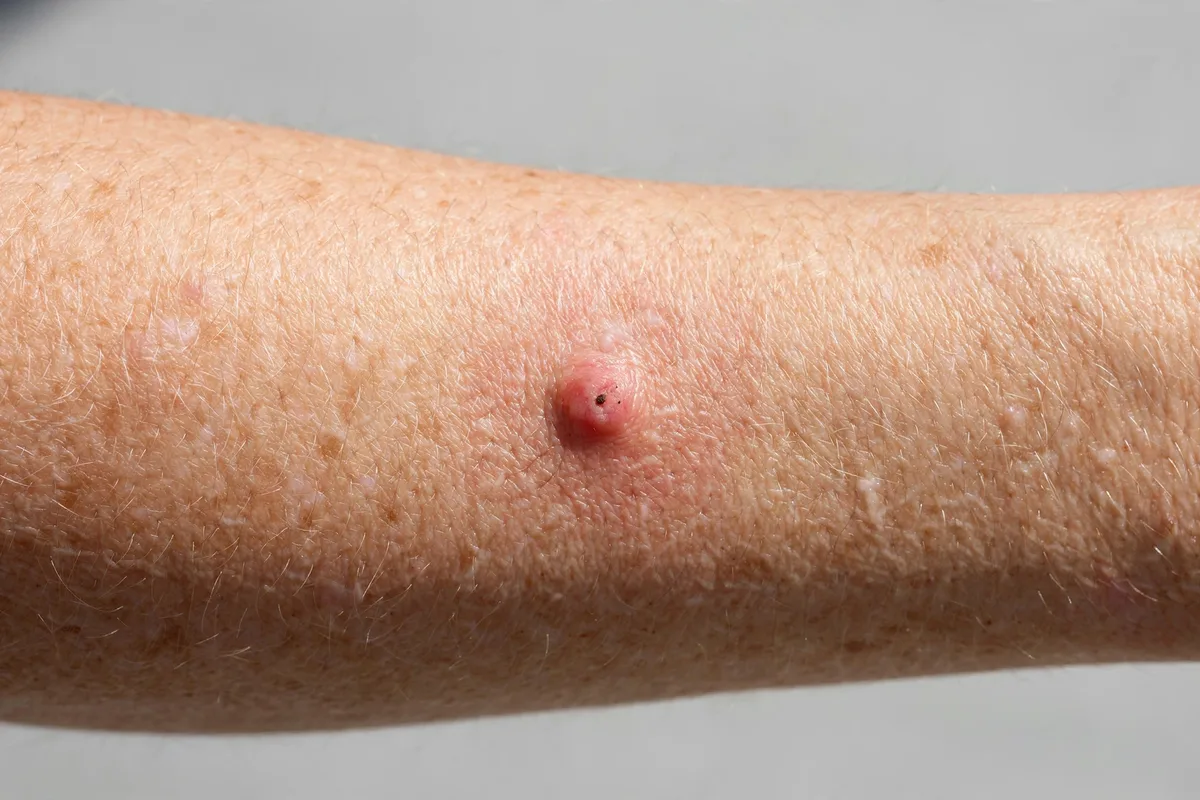
Redness, warmth, and swelling can be inflammatory rather than infectious. Infection is more concerning when pain is progressively increasing, redness keeps expanding while the person feels ill, pus or drainage develops, red streaking appears, or fever occurs. Scratching can damage the skin barrier and increase secondary infection risk.
Record the time of the sting, number of stings, whether a stinger was removed, how quickly symptoms started, and whether symptoms stayed local. This information is particularly important if an allergist later evaluates venom allergy.
Children, older adults, pregnant people, people taking beta blockers or other cardiovascular medicines, and anyone with a previous systemic sting reaction may warrant earlier clinician advice. People with a prescribed epinephrine auto-injector should keep it accessible and know their emergency plan.
Avoid disturbing hives, wear closed shoes outdoors, and use caution around flowering plants and open sweet drinks. If bees repeatedly enter a building or a hive is in a high-risk location, use an experienced beekeeper or appropriate pest professional rather than improvised removal.
Clinicians separate a local toxic/inflammatory reaction from systemic IgE-mediated allergy and from secondary infection. A history of symptoms away from the sting site, especially respiratory or cardiovascular symptoms, is more important than local swelling size. Recurrent systemic reactions may lead to allergy referral and discussion of venom immunotherapy.
Not reliably. A retained stinger and a witnessed bee are much stronger clues than the shape of a red bump.
Pain often improves within hours, while itching and swelling may last several days. Large local reactions can take longer but should trend toward improvement.
No. Antibiotics do not treat an ordinary inflammatory or allergic reaction and should not be used without a clinical indication. Seek medical assessment if infection signs develop.
No. A large local reaction can be impressive without affecting breathing or circulation. Emergency care is needed for systemic symptoms or airway involvement.
Keep the diagnosis open. Focus on safe first aid, the exposure setting, symptom trajectory, and warning signs. Skin appearance overlaps widely among bites, stings, dermatitis, and infection.
Bring the number and timing of stings, any photo of the insect if safely obtained, when symptoms began, treatments used, and whether there is a prior history of systemic reaction.

A large local reaction can extend well beyond the immediate sting site. Swelling may involve much of a hand, forearm, foot, or lower leg and can become more noticeable over the first 24–48 hours. This is different from anaphylaxis because the reaction remains centered around the sting rather than causing dangerous breathing, circulation, or widespread systemic symptoms. Even so, very large swelling can interfere with movement, sleep, or daily activity and may justify pharmacist or clinician advice.
If swelling is developing on a finger, hand, foot, or ankle, remove rings, tight watches, bracelets, or restrictive footwear early. Elevating the limb can reduce discomfort. Use photographs or a simple measurement to track whether swelling is stabilizing. A reaction that continues to expand while pain becomes more severe, fever develops, or the person feels increasingly unwell should be reassessed rather than automatically attributed to allergy.
Multiple stings deserve more caution than a single routine sting because the total venom exposure is higher. The threshold for medical evaluation should be lower after numerous stings, particularly in children, older adults, people with low body weight, or anyone who develops vomiting, severe headache, muscle symptoms, dizziness, weakness, or confusion. Do not spend time counting every puncture if the person is becoming unwell; move to safety and seek urgent care.
Stings inside the mouth or throat are also higher risk because swelling in a confined airway can become dangerous even without classic anaphylaxis. A person with oral or throat swelling, altered voice, difficulty swallowing, or breathing changes needs emergency assessment.
A previous systemic reaction to a bee sting changes future planning. An allergist may review the history, determine whether testing is appropriate, discuss epinephrine, and in selected cases consider venom immunotherapy. The purpose of allergy assessment is not to predict the size of every future local reaction; it is to reduce the risk from systemic venom allergy. A history of only local swelling does not automatically mean a future sting will cause anaphylaxis.
If epinephrine has been prescribed, make sure household members know where it is stored and how to use it. Check expiration dates and replace used or expired devices according to the prescriber’s guidance. Emergency plans should be practical enough to follow quickly rather than dependent on identifying the exact insect first.
Stings near the eyelid, eye surface, mouth, tongue, or throat require more caution because even localized swelling can affect vision or the airway. Do not attempt to remove a deeply embedded object from the eye. If a stinger appears to involve the eye itself, protect the eye from rubbing and obtain urgent professional evaluation.
For stings elsewhere on the face, watch the person’s breathing and swallowing rather than judging urgency from facial appearance alone. Facial tissues can swell dramatically from a local reaction, but tongue swelling, throat tightness, wheezing, faintness, or rapidly evolving whole-body symptoms are the emergency features.
Children often become frightened by the sudden pain, and crying can make it difficult to judge breathing symptoms. Move the child to a calm safe location, look for a visible stinger, and observe whether breathing and speech return to normal as distress settles. New wheezing, persistent cough, hoarse voice, repeated vomiting, unusual sleepiness, collapse, or swelling of the tongue or lips needs urgent attention.
Medication dosing in children must be age- and weight-appropriate. Do not estimate an adult dose. A pharmacist or pediatric clinician can help when symptoms are more than mild or when the child has asthma, severe allergies, or other medical conditions.
Bee venom causes inflammation immediately, so redness, warmth, tenderness, and swelling during the first hours are expected and do not automatically mean bacterial infection. Secondary infection is more likely when the skin has been scratched or damaged and symptoms evolve later toward increasing pain, purulent drainage, fever, or progressive spreading redness associated with illness.
This distinction prevents unnecessary antibiotics while still identifying complications early. If the reaction initially improves and then becomes significantly more painful or begins draining, that change is more concerning than stable swelling that simply takes several days to resolve.

Hands and feet can become functionally uncomfortable even when the reaction is only local. Remove constricting jewelry or footwear early, elevate the limb when resting, and check circulation beyond the swollen area. Numbness, severe color change, inability to move a digit normally, or rapidly increasing pressure-like pain deserves prompt assessment rather than simply adding more ice or topical medication.
Promptly remove a visible honey bee stinger, use gentle local care, and monitor the whole person rather than the skin alone. The key safety distinction is local swelling versus symptoms affecting breathing, circulation, consciousness, or multiple body systems.
StingHelp provides educational information and does not diagnose bites, stings, allergy, infection, or vector-borne disease. Seek professional care for severe, unusual, or worsening symptoms.
Immediate pain followed by later swelling is typical of venom injection. Anaphylaxis often develops rapidly, although timing can vary. Infection usually evolves later with increasing tenderness, pus, fever, or worsening redness rather than appearing instantly at the moment of the sting.
If stings are occurring repeatedly around one location, look for a nearby hive or flight path without approaching it. Do not spray indiscriminately around pollinators. Structural colonies or swarms should be handled by qualified local professionals.
Watch breathing, voice, swallowing, dizziness, vomiting, hives away from the sting, and the ability to use the affected limb. Take off rings early if a finger or hand is swelling. Any rapid systemic deterioration is an emergency.
Do not exceed label doses or combine products that contain the same active ingredient. Sedating antihistamines can impair driving and increase fall risk. Topical products should not be placed in the eye, mouth, or on large areas of broken skin unless a clinician specifically recommends it. For children, pregnancy, breastfeeding, or complex medical histories, individualized pharmacist or clinician advice is safer than copying an adult regimen from the internet.
The important management question is usually whether venom allergy or a complication is occurring. Exact bee species can matter for allergy follow-up, but emergency care should never be delayed for insect identification.
Write down the exposure time, body location, pain level, itch level, and any treatment used. Take one photograph now and another only if there is meaningful change. Measure swelling in the same way each time. Note whether the person can eat, drink, walk, sleep, and breathe normally. If function is deteriorating, the threshold for professional evaluation should be lower.
Dr. Jones oversees StingHelp’s clinical verification process. Every guide is systematically evaluated against active Centers for Disease Control and Prevention (CDC), Environmental Protection Agency (EPA), and American Academy of Allergy, Asthma & Immunology (AAAAI) medical consensus standards to ensure symptom distinctions and care recommendations are clinically sound.
Explore physician-reviewed first-aid procedures, identification clues, and symptom comparisons for other common outdoor bites and stings.

You have just been stung, and your first instinct is to look for the stinger. Do wasp stings leave a stinger? No, they do…

# Are Yellow Jackets Active at Night? The short answer is no, yellow jackets are not really active at night. These wasps are daytime…

Finding a gray, umbrella-shaped nest hanging under your porch eave can trigger an instant question: are paper wasps aggressive, and is my family in…